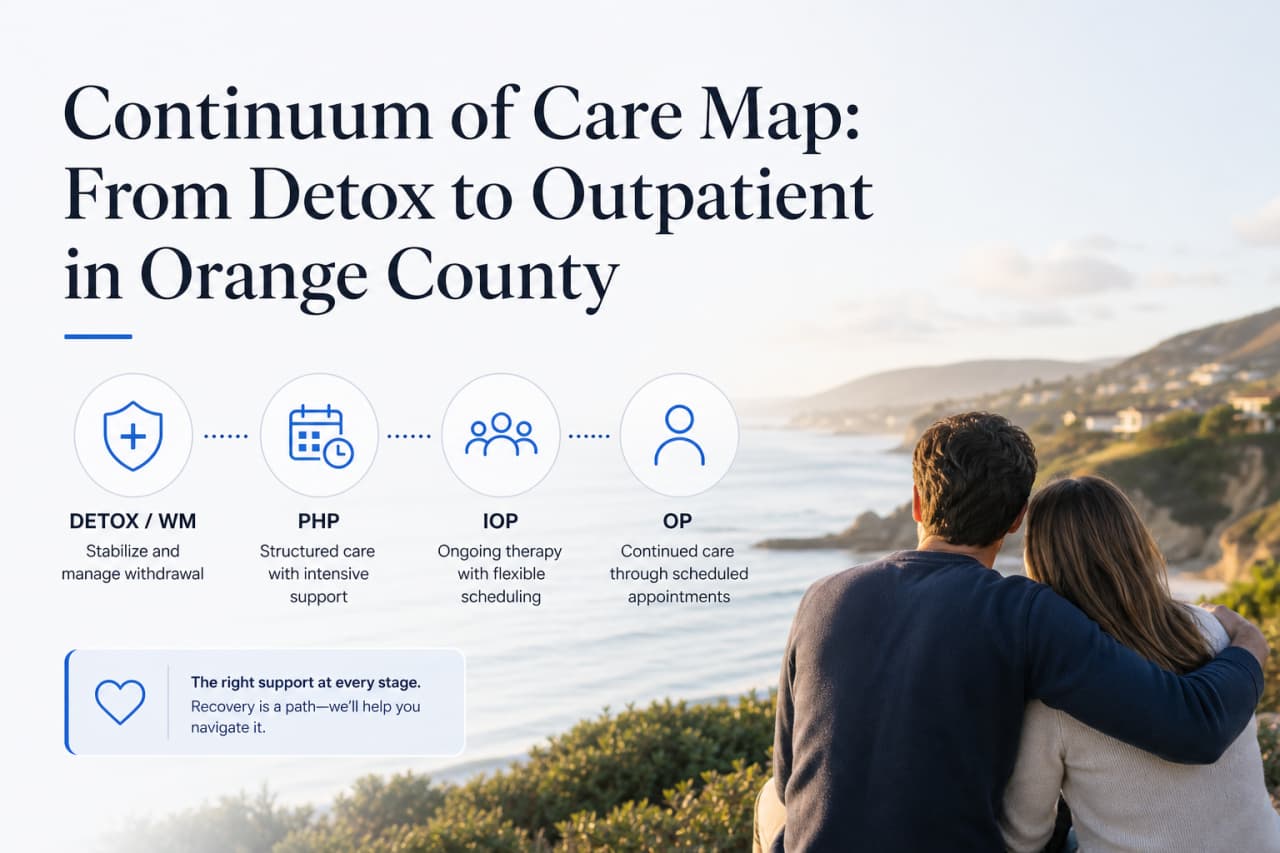
Discharge notes after IOP or PHP often name a meeting or two, then the plan stalls once work, traffic, and evening fatigue hit the calendar. The peer support groups Orange County after treatment options that last are ones you can reach on time, with rules you grasp, and a culture that does not fight your current care plan. Screen meetings first. Test the room. Plan the logistics before you treat any listing as a finished answer.
Peer support can give regular contact with people who have relevant lived experience. It works beside continuing clinical care when that care is still recommended. Your job is to find a group that matches your goals, schedule, privacy needs, and stage after intensive outpatient or partial hospitalization.
Peer groups do not provide emergency care. Contact emergency services if you may harm yourself or someone else, or if another immediate safety risk is present.
What peer support can add after IOP or PHP
A useful peer group adds recurring contact, practical ideas, and accountability between formal appointments. It can also put structure into evenings or weekends that used to revolve around treatment sessions. According to SAMHSA's peer support resource, peers draw on lived experience to help people facing similar situations.
Clinical care and peer support do different work. A clinician can assess symptoms, diagnose conditions, manage treatment, and respond to medical concerns. A peer can share experience, notice your absence, or explain how they handled a hard stretch. NIDA's principles of effective treatment state that treatment plans should be reviewed and modified as a person's needs change. Your peer routine belongs in that review.
That distinction matters.
Group formats that match different recovery goals
Choose by structure and purpose before you chase a popular name. A familiar meeting title will not help if the approach conflicts with your care plan or you cannot attend at the scheduled hour. People leaving PHP or IOP often need different support than someone seeking a first community connection.
| Group format | What you may encounter | Question to ask |
|---|
| Recovery mutual-aid meeting | A recurring format led by members, often with readings or personal sharing | Does the group's approach match my current goals? |
| Facilitated peer group | A peer leader guides discussion and manages meeting boundaries | What training, supervision, and complaint process does the facilitator have? |
| Mental health peer group | Discussion centered on symptoms, daily life, treatment experiences, or social connection | Does the group address my concern specifically or discuss mental health more broadly? |
| Dual-focus group | Space for both substance use disorder and mental health concerns | Can members discuss both issues without one being dismissed? |
| Faith-centered group | Religious beliefs or spiritual practices shape the meeting | Am I comfortable with the beliefs and participation expectations? |
| Alumni or aftercare community | Connection based on a shared treatment program or discharge experience | How long can former participants remain involved? |
Ask how the group defines participation. Some meetings center abstinence. Others focus on harm reduction, mental health, family concerns, or general wellness. The label alone will not tell you which one applies.
Evaluating a group before you commit
Use two passes. First confirm the meeting is real, current, accessible, and open to you. Then watch how people behave once the meeting starts. A polished listing cannot show how leaders handle conflict, confidentiality concerns, or advice that drifts into clinical care.
| Evaluation point | What to check | Why it affects fit |
|---|
| Purpose | The group can explain whom it supports and what members do during meetings | A defined purpose keeps expectations clear |
| Leadership | You know who leads, how leaders are selected, and who handles concerns | Clear responsibility gives you a path when problems arise |
| Confidentiality | The opening rules explain privacy, photos, recordings, and outside contact | Community groups may follow different privacy rules from licensed clinics |
| Boundaries | Members are not pressured to lend money, date, buy services, or share private details | Peer connection depends on voluntary participation |
| Clinical limits | Leaders do not diagnose people or direct medication changes | Medical decisions belong with licensed professionals |
| Conflict response | Leaders stop threats, harassment, discrimination, or repeated interruptions | Rules mean little if no one applies them |
| Access | The location, online platform, language, and physical access work for you | A group you cannot reliably reach will not provide recurring contact |
| After-meeting culture | Social contact remains respectful and does not create pressure | Many boundary problems appear outside the formal meeting |
Give an ordinary group more than one visit before you judge its usual culture. One odd night can mislead you. You do not owe a second visit after harassment, coercion, a privacy breach, or another serious boundary problem.
Fit earns trust over time.
Searching Lake Forest and Orange County for peer groups after treatment
Start with the format you need, then narrow by location and schedule. Searching only for a nearby recovery meeting can surface groups with very different rules. Add terms such as peer-led, mental health, dual-focus, abstinence, harm reduction, faith-centered, open meeting, or online meeting.
For a Lake Forest search, pair the location with the day, time, and format you can actually attend. Use an official group source or SAMHSA's Find Support page as a starting point. Confirm every listing through the organizer or venue, because meeting times, access rules, and locations change.
Write down the purpose and format you want before you open a search page. Search Lake Forest and the Orange County spots you can reach at the meeting hour. Confirm the date, start time, address, online link, and open or closed status. Ask whether registration, identification, payment, or an intake call is required. Keep a backup for cancellations, work conflicts, or transportation problems. After you attend, record what you saw instead of trusting only your first emotional reaction.
A directory says a meeting may exist. Direct confirmation tells you if you can attend.
Local logistics that decide whether you keep attending
The meeting has to fit your real week. Test the route during the same time window as the meeting rather than checking a map on a quiet afternoon. Factor in parking, building access, public transportation, work hours, child care, and the trip home.
| Logistics question | Practical test | Backup plan |
|---|
| Can I arrive on time? | Travel the route during the scheduled meeting window | Identify a later meeting or online option |
| Can I enter the building? | Confirm the room, entrance, accessibility, and check-in rules | Save the organizer's contact information |
| Does it fit work? | Add travel and post-meeting time to your calendar | Choose a second day that does not depend on leaving work early |
| Can I protect my privacy online? | Test headphones, camera settings, and a private location | Attend without video if group rules permit |
| What happens if I miss it? | Ask if the group has another meeting or check-in option | Put your next available meeting on the calendar |
People often pick a meeting by distance and ignore timing. In Orange County, the useful measure is the full door-to-door routine at the scheduled hour. A group five minutes closer on a map can still be harder to keep if parking or entry is unclear.
Test the route.
Warning signs that call for leaving a group or getting clinical help
Leave or seek outside guidance when a group pressures you to ignore clinical advice, disclose private information, give money, enter a relationship, or cut off people who are not part of the group. A peer can describe a personal experience with medication. That person should not tell you to start, stop, or change medication.
Treat these as hard stops. Leaders dismiss reports of harassment or threats. Members are shamed for symptoms, a return to use, medication, identity, or treatment choices. The group promises a cure or guaranteed result. A leader presents personal opinion as medical or legal advice. Members face pressure to buy products, services, housing, or coaching. The group records meetings or shares names without clear permission. One person controls outside relationships or discourages contact with clinicians and family.
Worsening depression, mania, psychosis, trauma symptoms, withdrawal, or thoughts of self-harm require clinical attention. The NIMH guide to finding help lists options for routine and urgent mental health support, including the 988 Suicide and Crisis Lifeline. Contact your clinician or emergency services based on the level of risk.
Boundaries matter.
Connecting peer support to continuing care
Build a simple bridge between peer contact and your formal plan. You control what personal information moves between those settings. Do not assume a community group follows the same confidentiality rules as an outpatient clinic. Ask before sharing names, diagnoses, medication details, or treatment records.
| Planning area | Decision to make | What to document |
|---|
| Attendance | Choose a realistic meeting frequency | Days, times, locations, and backup meetings |
| Privacy | Decide what you will share with peers | Topics you want to keep for clinical sessions |
| Care coordination | Choose what your clinician needs to know | Changes in symptoms, attendance, sleep, or substance use |
| Early warning signs | Name signs that your current plan needs review | Missed appointments, isolation, cravings, or worsening symptoms |
| Response | Identify whom you will contact at each level of concern | Peer contact, clinician, trusted family member, or emergency service |
If you receive outpatient care through Rize OC, bring specific observations to your appointment. Report what happens before, during, and after the meeting. Concrete details give your care team more to work with than saying a group felt good or bad.
A first-month plan for peer support
Treat the first month as a structured trial, not an open-ended hunt. The outline below is an example, not a clinical prescription. Change it with your care team if symptoms, work demands, family duties, or transportation make another pace safer.
Week 1 is for defining the format you want, verifying two meeting options plus one backup, and checking access rules before you show up. Attend in week 2 and take brief notes afterward on structure, leadership, boundaries, travel time, and how the meeting affected the next day. Revisit the stronger option during week 3 and ask one practical question about confidentiality, participation, or handling conflict. By week 4, review the pattern with your clinician or another trusted support person, then choose a repeatable schedule, keep searching, or pause a group that does not fit.
Track observable facts. Note whether you attended, arrived on time, felt pressured, received unwanted advice, or connected with someone who respected your boundaries. Those details help you decide without expecting a single meeting to prove everything.
A repeatable plan is easier to follow.
Common Questions
How many peer meetings should I attend each week?
No universal number fits every person after IOP or PHP. Choose a frequency you can keep without missing clinical appointments, work, sleep, or family responsibilities. Review that schedule if symptoms worsen or attendance starts to feel compulsory.
Can an online peer group count as community support?
An online group can provide recurring peer contact when travel, health, work, or child care blocks in-person attendance. Check the group's privacy rules, camera expectations, meeting security, and plan for disruptions. Some people use online access as a backup while keeping one local connection.
Can I attend if abstinence isn't my current goal?
You can search for groups whose stated purpose matches your current goals, including harm reduction or mental health peer support. Ask directly before attending. Do not assume every substance-related group uses the same definition of recovery or participation.
Can a family member or friend attend with me?
Attendance depends on the group's open or closed status. Open meetings may allow visitors, while closed groups limit participation to people who meet stated criteria. Confirm the rule before bringing someone, and ask the person you support for permission.
Can peer support replace therapy or outpatient treatment?
It can add community and recurring contact beside a clinical plan. Discuss any reduction in formal care with the professional managing your treatment.
Have questions about pairing peer support with outpatient care after PHP or IOP? Reach the Rize OC team with your meeting shortlist, schedule limits, and questions about safety or format so the conversation stays concrete.